
A recent study published in the Journal of Perinatology investigated differences across Level III neonatal intensive care units that share the same designation from the American Academy of Pediatrics. Researchers aimed to describe the range of patient populations, available services, and resulting health outcomes while identifying possible subgroups within this category of care facilities.
The analysis drew on retrospective data from multiple states including Florida, Michigan, Oregon, Pennsylvania, and South Carolina. By linking hospital discharge records with vital statistics information, the team examined patterns across a large cohort of units. This approach allowed comparison of structural features, clinical practices, and patient results without relying on prospective observation.
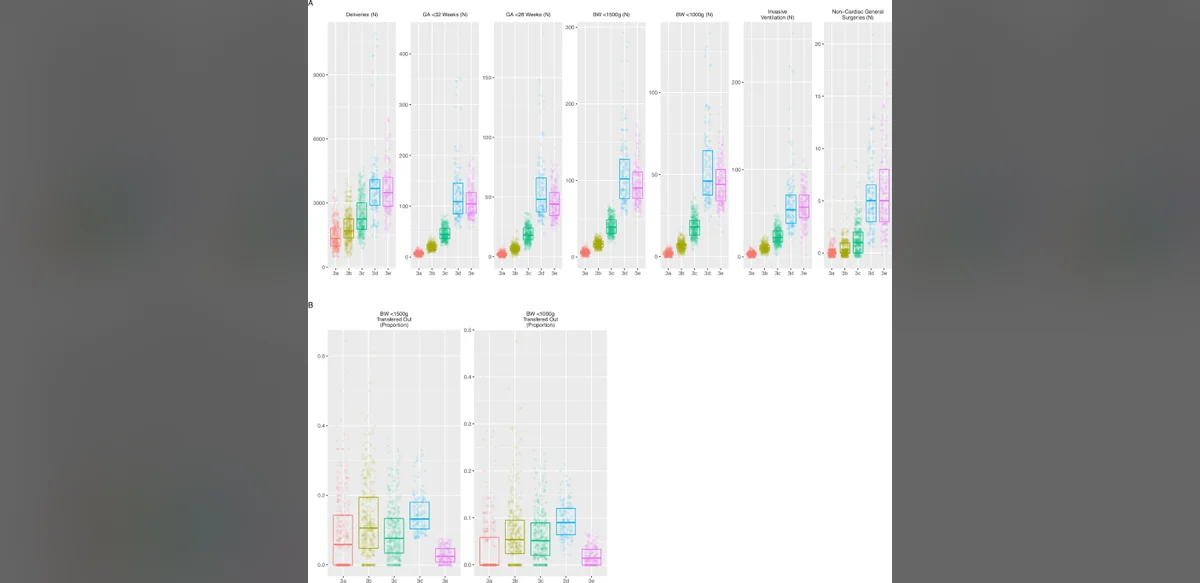
Findings highlighted notable variation in the characteristics of infants admitted to these units as well as in the range of specialized services offered. Some facilities managed higher volumes of complex cases while others focused on different mixes of prematurity and medical conditions. The study also explored how these differences translated into measurable outcomes such as survival rates and length of stay.
Through statistical methods the investigators grouped the units into sub-classes that shared similar profiles. These groupings revealed that not all Level III units operate in identical ways despite holding the same formal designation. Outcome comparisons across the identified sub-classes showed measurable distinctions that could inform future quality improvement efforts.
The work underscores the importance of recognizing internal diversity within a single level of care designation. Policy makers and hospital administrators may use such insights to tailor resources and standards more precisely. Further research could build on these observations by including additional regions or examining trends over longer periods.
Overall the study contributes to a deeper understanding of neonatal intensive care delivery in the United States. It demonstrates how administrative data sources can illuminate practice variation and support evidence based refinements in newborn medicine. Continued attention to these differences may help optimize care for vulnerable infants across diverse settings.


